
Sickle-Cell Disease
Introduction to Sickle-Cell Disease
Sickle-cell disease is a complex multisystem genetic disorder characterized by chronic hemolytic anemia, recurrent vaso-occlusive crises, progressive organ injury, and severe systemic complications. It represents one of the most prevalent monogenic diseases globally and has a particularly high burden in populations originating from sub-Saharan Africa, the Middle East, India, and the Mediterranean region.
The disease was first described in 1910 when abnormal crescent-shaped erythrocytes were identified in affected individuals. Subsequent discoveries in molecular biology revealed that sickle-cell disease is caused by a mutation in the β-globin gene, making it one of the first disorders recognized as a “molecular disease.” Although major advances have improved the understanding of its molecular and cellular mechanisms, therapeutic management remains challenging, and only a limited number of targeted pharmacological treatments are currently available.
Sickle-cell disease causes repeated episodes of vascular obstruction, tissue ischemia, inflammation, oxidative stress, and chronic hemolysis, leading to cumulative damage in multiple organs including the lungs, kidneys, brain, heart, and liver. Disease severity varies considerably between individuals because of genetic modifiers, environmental influences, and differences in fetal hemoglobin expression.
Classification of Sickle-Cell Disease
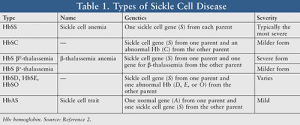
The term sickle-cell disease includes a group of inherited hemoglobinopathies associated with the production of abnormal hemoglobin S (HbS). The most common and severe form is sickle-cell anemia, which occurs in individuals homozygous for the βS allele.
Several major genotypes are associated with sickle-cell disease:
- Sickle-cell anemia (HbSS): homozygous inheritance of HbS
- Hemoglobin SC disease (HbSC): co-inheritance of HbS and hemoglobin C
- HbS/β-thalassemia: inheritance of HbS with β-thalassemia mutations
- Rare compound heterozygous variants involving other abnormal hemoglobins
Among individuals of African ancestry, HbSS accounts for the majority of sickle-cell disease cases, while HbSC disease and HbS/β-thalassemia represent important additional clinical forms. Disease severity differs according to genotype, residual β-globin production, fetal hemoglobin concentration, and coexisting hematologic traits.
Molecular Basis and Pathophysiology
Genetic Mutation and Hemoglobin S Polymerization
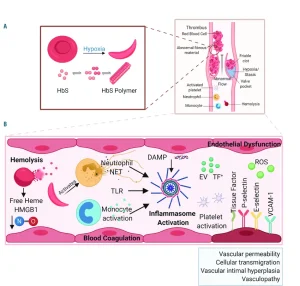
Sickle-cell disease originates from a single nucleotide substitution in the β-globin gene. This mutation replaces glutamic acid with valine at the sixth position of the β-globin chain, creating a hydrophobic region on the hemoglobin molecule.
Under deoxygenated conditions, abnormal hemoglobin S molecules aggregate and polymerize inside erythrocytes. These rigid polymers distort red blood cells into the characteristic sickle shape, reducing membrane flexibility and promoting cellular dehydration, oxidative injury, and premature destruction.
The severity of hemoglobin S polymerization depends on several major factors:
- Degree and duration of deoxygenation
- Intracellular HbS concentration
- Presence of fetal hemoglobin (HbF)
- Erythrocyte hydration status
- Co-inherited genetic modifiers such as α-thalassemia
Higher concentrations of fetal hemoglobin significantly inhibit HbS polymer formation and reduce disease severity.
Major Pathophysiological Mechanisms
Vaso-Occlusion and Ischemia-Reperfusion Injury

Acute vaso-occlusive events represent a hallmark of sickle-cell disease. Polymerized erythrocytes become rigid and adhere abnormally to endothelial cells, leukocytes, and platelets within the microcirculation. These adhesive interactions lead to vascular obstruction, impaired blood flow, tissue ischemia, and severe pain crises.
Inflammation plays a central role in initiating vaso-occlusion. Endothelial activation increases the expression of adhesion molecules, including selectins and vascular adhesion proteins, facilitating interactions between blood cells and vessel walls.
Repeated cycles of ischemia and reperfusion trigger:
- Oxidative stress
- Cytokine release
- Leukocyte activation
- Endothelial dysfunction
- Progressive organ injury
Bone marrow infarction and fat embolization can further worsen vascular obstruction, especially in pulmonary tissues, contributing to acute chest syndrome.
Hemolytic Anemia and Nitric Oxide Depletion
Chronic intravascular hemolysis is another critical mechanism in sickle-cell disease. Continuous destruction of erythrocytes releases free hemoglobin and arginase into plasma circulation.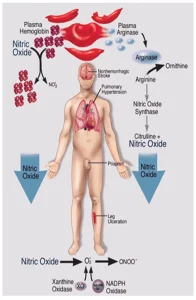
Free plasma hemoglobin scavenges nitric oxide, a major endothelial vasodilator responsible for regulating vascular tone, platelet activation, and inflammatory signaling. Reduced nitric oxide bioavailability contributes to:
- Pulmonary hypertension
- Endothelial dysfunction
- Vasculopathy
- Hypercoagulability
- Increased vascular stiffness
Additionally, erythrocyte arginase depletes plasma arginine, further impairing nitric oxide synthesis and amplifying vascular injury.
Chronic hemolysis is strongly associated with complications such as:
- Pulmonary hypertension
- Leg ulcers
- Priapism
- Cholelithiasis
- Progressive vascular disease
Epidemiology and Global Burden
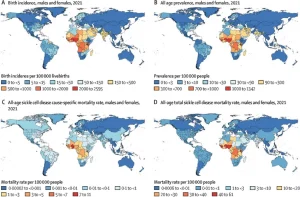
The worldwide distribution of sickle-cell disease reflects evolutionary selection by malaria. Carriers of the sickle-cell trait have partial protection against severe infection caused by Plasmodium falciparum, leading to high frequencies of the HbS gene in malaria-endemic regions.
The disease burden is greatest in sub-Saharan Africa, where hundreds of thousands of affected children are born annually. Limited diagnostic infrastructure, inadequate neonatal screening, and restricted access to healthcare contribute to extremely high childhood mortality rates.
Additional high-prevalence regions include:
- India
- Saudi Arabia
- Mediterranean countries
- Caribbean populations
- North and South America due to migration
International public health organizations now recognize sickle-cell disease as a major global health priority requiring expanded screening, early diagnosis, and long-term management programs.
Phenotypic Heterogeneity
Clinical manifestations vary greatly among patients with sickle-cell disease. Some individuals experience relatively mild symptoms, whereas others develop recurrent painful crises, severe organ dysfunction, and early mortality.
Major genetic modifiers include:
- Fetal hemoglobin concentration
- Co-inherited α-thalassemia
- Polymorphisms affecting inflammatory pathways
- Variants influencing vascular regulation
Environmental factors such as infections, climate, hypoxia, air pollution, and socioeconomic conditions also influence disease severity.
Elevated fetal hemoglobin concentrations are strongly associated with:
- Reduced vaso-occlusive crises
- Lower stroke risk
- Decreased hemolysis
- Improved survival
Clinical Manifestations and Complications
Acute Pain Crises
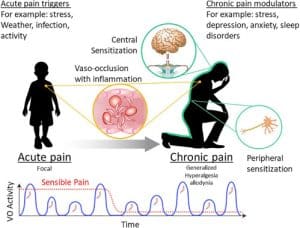
Vaso-occlusive pain episodes are the most frequent clinical complication and a major cause of hospitalization. These crises result from microvascular obstruction and tissue ischemia caused by sickled erythrocytes.
Pain episodes commonly affect:
- Bones
- Joints
- Chest
- Abdomen
- Extremities
Management primarily relies on:
- Opioid analgesics
- Hydration therapy
- Oxygen supplementation
- Anti-inflammatory medications
- Supportive care
Despite advances in supportive management, no therapy completely prevents acute pain crises.
Acute Chest Syndrome
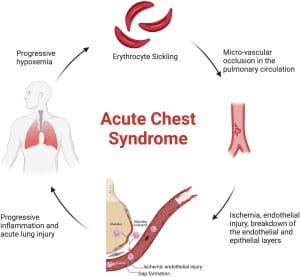
Acute chest syndrome is a severe pulmonary complication characterized by new pulmonary infiltrates, respiratory distress, fever, and hypoxemia.
Its pathogenesis involves:
- Pulmonary vaso-occlusion
- Infection
- Fat embolization
- Inflammation
Treatment includes:
- Broad-spectrum antibiotics
- Oxygen therapy
- Bronchodilators
- Blood transfusion
- Exchange transfusion in severe cases
Acute chest syndrome remains a leading cause of mortality in sickle-cell disease.
Neurological Complications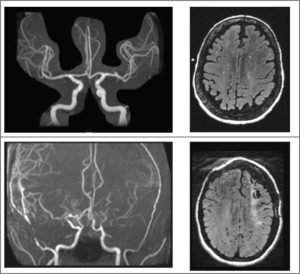
Stroke is a major complication, especially in children with sickle-cell anemia. Cerebrovascular injury results from progressive vasculopathy involving large intracranial arteries.
Risk factors include:
- Severe anemia
- Endothelial dysfunction
- Chronic inflammation
- Increased cerebral blood flow velocity
Transcranial Doppler ultrasound screening helps identify high-risk children, allowing preventive chronic transfusion therapy to significantly reduce stroke incidence.
Silent cerebral infarctions are also common and may cause long-term cognitive impairment even without overt neurological symptoms.
Pulmonary Hypertension
Pulmonary hypertension is increasingly recognized as a serious complication in adolescents and adults with sickle-cell disease. Chronic hemolysis, nitric oxide depletion, endothelial dysfunction, and vascular remodeling contribute to elevated pulmonary artery pressure.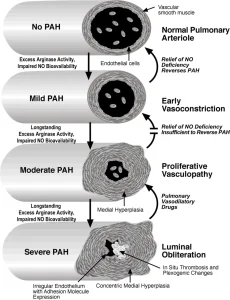
Pulmonary hypertension is associated with:
- Reduced exercise tolerance
- Right heart dysfunction
- Increased mortality
- Progressive cardiopulmonary disease
Management may involve:
- Hydroxyurea therapy
- Oxygen support
- Chronic transfusion programs
- Pulmonary vasodilator therapies
Renal and Cardiovascular Complications
Chronic kidney injury is highly prevalent because the renal medulla promotes HbS polymerization through hypoxia and hyperosmolarity.
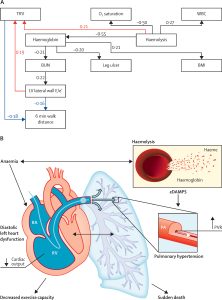
Renal manifestations include:
- Proteinuria
- Hematuria
- Glomerular hyperfiltration
- Chronic kidney disease
- End-stage renal failure
Cardiac complications include:
- Left ventricular hypertrophy
- Diastolic dysfunction
- Pulmonary vascular disease
- Heart failure
These complications substantially increase morbidity and mortality in adult patients.
Diagnosis and Screening
Diagnosis of sickle-cell disease relies on hemoglobin analysis techniques such as:
- Hemoglobin electrophoresis
- High-performance liquid chromatography (HPLC)
- DNA-based molecular testing
- Mass spectrometry
Universal neonatal screening programs have significantly improved survival by enabling:
- Early prophylactic penicillin therapy
- Vaccination
- Parent education
- Monitoring for complications
Prenatal genetic screening also helps identify at-risk pregnancies.
Current Therapeutic Approaches
Hydroxyurea Therapy
Hydroxyurea is currently one of the most effective disease-modifying therapies for sickle-cell disease.
Its therapeutic effects include:
- Increased fetal hemoglobin production
- Reduced hemolysis
- Lower leukocyte and platelet counts
- Decreased endothelial adhesion
- Reduced frequency of vaso-occlusive crises
Clinical studies have shown that hydroxyurea decreases:
- Pain episodes
- Acute chest syndrome
- Hospitalization
- Need for transfusion
Long-term treatment may also improve survival.
Blood Transfusion and Iron Chelation
Blood transfusion plays a major role in both acute and chronic complications.
Transfusion therapy reduces circulating HbS concentration and improves oxygen delivery. Exchange transfusion is particularly useful in:
- Stroke
- Severe acute chest syndrome
- Multi-organ failure
Chronic transfusion causes iron overload, requiring iron chelation therapy with agents such as:
- Deferasirox
- Deferoxamine